Executive Summary
Sciatica is pain that travels along the sciatic nerve — the longest, thickest nerve in your body — usually from your lower back or buttock down the back of one leg. It is extremely common, affecting a large proportion of people at some point in their lives.
Here is what matters most: sciatica is a symptom, not a diagnosis on its own — it always has an underlying cause, and finding that cause changes what treatment actually helps. The most common cause is a lumbar disc herniation, but sciatica can also come from spinal stenosis, a slipped vertebra (spondylolisthesis), or, less often, a tight piriformis muscle deep in the buttock pressing on the nerve. Many people improve substantially within 6–12 weeks, especially when a disc is the cause; stenosis-related symptoms often improve more slowly. A small number of red flag symptoms mean you should seek care immediately rather than waiting — this article tells you exactly what they are.
Red Flags
⚠ See a doctor immediately — the same day, not a routine appointment — if you have:
- Loss of bladder or bowel control, or new difficulty starting urination
- Numbness in the area between your legs, inner thighs, or around your genitals ("saddle numbness")
- Weakness in both legs, especially if it's getting worse
- Sciatica in both legs, or alternating sides
- Fever combined with severe back or leg pain, especially with a history of recent infection, IV drug use, or a weakened immune system
- A history of cancer, combined with new, severe back pain
- Sciatica that started after a significant fall or accident
These can be signs of cauda equina syndrome, a spinal infection, a fracture, or a spinal tumor — all genuine emergencies that need same-day evaluation.
A progressive motor deficit — leg or foot weakness that is clearly getting worse over days, even without the full picture above — is also a reason to seek urgent evaluation rather than continuing routine conservative care — same-day if the weakness is worsening quickly or is severe (for example, foot drop).
Read the full article18 min · causes, tests, treatment, exercises, questions
Introduction
"Sciatica" is one of the most searched, most misunderstood terms in back pain. People often use it to describe any pain in the buttock or leg, but true sciatica has a specific pattern and a specific cause — and knowing the difference matters, because treating "leg pain" in general is not the same as treating the actual nerve problem causing it.
This article explains what the sciatic nerve actually is, the real causes of sciatica, how to tell it apart from other kinds of leg pain, when it's a genuine emergency, and what the evidence actually supports for treatment — separate from the many home remedies and myths that surround this condition.
Normal Anatomy: The Sciatic Nerve
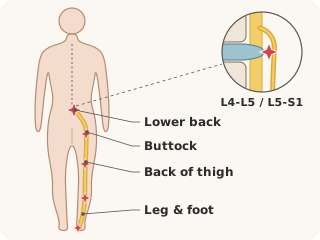
The sciatic nerve is formed from the joining of several nerve roots — typically L4, L5, S1, S2, and S3 — that come together deep in your pelvis, just below the piriformis muscle in your buttock. From there, it's a single thick nerve, roughly the width of your thumb, running down the back of your thigh, before splitting near your knee into branches that continue into your lower leg and foot.
It is the longest and widest nerve in the human body, which is exactly why irritation anywhere along its path — from where its component nerve roots exit your spine, to where it passes through your buttock, to along your thigh — can cause pain that seems to travel a long distance from wherever the actual problem is.
This is the key idea behind sciatica: the pain is felt along the nerve's path, but the problem causing it is almost always somewhere else — usually in your lower spine, sometimes in your buttock muscle.
How Sciatica Develops
Sciatica happens when something irritates or compresses one or more of the nerve roots that form the sciatic nerve, or the nerve itself along its path. The most common underlying causes are:
- Lumbar disc herniation — by far the most common cause, especially in people under 50, where a herniated disc at the L4-L5 or L5-S1 level presses on or chemically irritates a nerve root. (See Carenyx's full article on slip disc for the detailed mechanism.)
- Spinal stenosis — a narrowing of the spinal canal, more common with age, that can compress the nerve roots forming the sciatic nerve, often causing pain that's worse with walking or standing and better with sitting or leaning forward.
- Spondylolisthesis — when one vertebra slips forward over the one below it, which can narrow the space available for nerve roots.
- Piriformis syndrome — when the piriformis muscle, which the sciatic nerve runs directly beneath (and in some people, partly through), becomes tight or spasms and irritates the nerve. This is a genuinely debated diagnosis in the medical literature — some specialists consider it under-recognized, while others consider it over-diagnosed as an explanation for buttock pain that actually has a different spinal cause. It's a real cause of sciatica-like pain in a genuine subset of patients, but it should be a diagnosis of exclusion — meaning spinal causes should usually be reasonably ruled out first.
- Rarely, a tumor, cyst, or infection can compress the nerve roots — one reason red flag symptoms (below) matter.
Risk Factors
- Age: most common between 30 and 50 for disc-related sciatica, and increasingly common with age for stenosis-related sciatica.
- Occupation: physically demanding jobs involving heavy lifting, prolonged driving, or whole-body vibration.
- Prolonged sitting: increases pressure on lower lumbar discs and, for some people, on the piriformis muscle directly.
- Diabetes: associated with an increased risk of sciatica, possibly related to effects on nerve and disc health.
- Smoking: linked to faster disc degeneration, one of sciatica's main underlying causes.
- Obesity: increases mechanical load on the lower spine.
Symptoms
True sciatica has a recognizable pattern, distinct from general back or buttock pain:
- Pain that radiates, typically from the lower back or buttock, down the back or side of one leg, sometimes reaching the calf or foot. It is usually one-sided.
- The leg pain is often worse than the back pain — a genuinely useful clue, since many other causes of back pain cause back pain that's worse than any leg symptoms.
- Numbness or tingling along the same path.
- Weakness in specific leg or foot movements, depending on which nerve root is involved (see Carenyx's slip disc article for the specific L5 and S1 patterns).
- Worse with sitting, coughing, or sneezing for disc-related sciatica; worse with walking or standing, better with sitting, for stenosis-related sciatica — this specific pattern difference is a genuinely useful clue to the underlying cause.
- A burning, shooting, or electric-shock quality to the pain, different from a dull ache — a feature that specifically suggests nerve involvement rather than a muscular or joint problem.
Sciatica is different from generalized lower back pain that stays in the back, and different from pain that only reaches the buttock or upper thigh without extending further down the leg — both of those patterns are more often muscular or joint-related than truly neural.
Diagnosis
Diagnosing sciatica itself is usually straightforward from the history and pattern of pain described above. The harder, more important question is why it's happening, because that changes treatment.
Your doctor's exam will typically include the same core elements described in Carenyx's slip disc article — the straight leg raise test, strength testing, reflex testing, and sensation testing — plus specific attention to how your symptoms change with position (worse walking vs. worse sitting is a genuinely useful clue between a disc cause and a stenosis cause).
As with a straightforward disc herniation, imaging is not automatically needed for every case of sciatica, particularly early on. It becomes appropriate when symptoms haven't improved after a reasonable period of conservative treatment, when red flags are present, or when the diagnosis is genuinely unclear between the possible causes above.
MRI Explained
An MRI for sciatica is looking for the same things described in detail in Carenyx's slip disc article — but with attention to a few additional possibilities depending on your specific symptom pattern:
- If your pain is worse walking, better sitting, the radiologist will specifically look at the width of your spinal canal and the nerve root openings (foramina) for narrowing consistent with spinal stenosis, not just disc herniation.
- If there's any suggestion of one vertebra having slipped over another, the report may specifically comment on spondylolisthesis and its grade (how far the vertebra has slipped).
- Piriformis syndrome does not reliably show up on a standard lumbar spine MRI — it's a muscular, not spinal, cause, and is usually a clinical diagnosis based on exam findings (tenderness over the piriformis, pain with specific hip movements) after spinal causes have been reasonably considered.
As with any spine MRI, the same core principle applies: findings must be correlated with your actual symptoms and exam, not read in isolation, because incidental disc and spinal changes are extremely common in people without any symptoms at all.
Telling Sciatica Apart From Other Conditions
Several other conditions can cause leg pain that gets mistaken for sciatica, and telling them apart matters because the treatment is genuinely different for each:
- Hip osteoarthritis: pain from an arthritic hip joint often radiates into the groin, outer thigh, or knee, and is typically worse with specific hip movements (like putting on socks or getting out of a car) rather than with sitting, coughing, or sneezing. Hip exam findings, not spine findings, usually explain it.
- Peripheral neuropathy: nerve damage from conditions like diabetes typically causes symmetrical numbness and tingling in both feet and lower legs, often described as "stocking-like," rather than the one-sided pattern along a single nerve's path that's typical of sciatica.
- Trochanteric bursitis: inflammation of a fluid-filled cushion at the outer hip causes pain specifically over the outer hip and thigh, tender to direct pressure, without the back-pain association or below-the-knee radiation typical of true sciatica.
- Vascular claudication: pain from reduced blood flow to the legs (often related to peripheral artery disease) is triggered by walking and relieved by rest — genuinely similar to stenosis-related sciatica's walking pattern, which is exactly why doctors check pulses in your feet and ask about cardiovascular risk factors when this pattern is present, not just assume a spinal cause.
None of this is meant for you to self-diagnose between these — it's meant to explain why your doctor's exam covers more ground than just your back, and why an accurate diagnosis, not just a symptom description, is what actually guides effective treatment.
Treatment Options
Treatment for sciatica depends significantly on its underlying cause, but shares a common general approach for most people:
First-Line: Conservative Treatment
- Staying appropriately active, avoiding prolonged bed rest — the same evidence that applies to disc herniation applies here.
- Anti-inflammatory medication as a first-choice pain reliever for most people, for a limited period. Take them only on a doctor's advice, especially if you have stomach, kidney, heart or BP problems or are pregnant. NICE advises against pregabalin/gabapentin and oral steroids for sciatica.
- Physiotherapy, tailored to the underlying cause — extension-based exercises tend to help disc-related sciatica, while flexion-based exercises and specific stretching often help stenosis-related sciatica more, which is exactly why an accurate diagnosis of the cause matters before starting a specific exercise program.
- For suspected piriformis syndrome specifically: targeted piriformis stretching and physiotherapy is the usual first approach, and a meaningful proportion of patients improve with this alone.
Second-Line: Injections
Epidural steroid injections can help disc- and stenosis-related sciatica in the short-to-medium term for some patients, with the same genuinely moderate evidence discussed in Carenyx's slip disc article. For suspected piriformis syndrome, a targeted piriformis muscle injection (sometimes guided by ultrasound) can be both diagnostic and therapeutic — meaningful relief after the injection supports that diagnosis.
When Surgery Is Considered
Surgical treatment, when appropriate, targets the specific underlying cause:
- For disc herniation: microdiscectomy, as detailed in Carenyx's slip disc article.
- For spinal stenosis: decompression surgery (laminectomy or a more limited, targeted decompression), which enlarges the space available for the compressed nerve roots.
- For spondylolisthesis with significant nerve compression or instability: decompression, sometimes combined with spinal fusion, depending on the specific situation.
As with disc-related sciatica generally, surgery is usually considered after an adequate trial of conservative treatment has not sufficiently helped, or sooner if red flag symptoms or significant progressive weakness are present.
Exercises
The right exercise approach genuinely depends on the underlying cause — this is one condition where "just do these back exercises" without knowing the cause can occasionally make things worse rather than better, which is exactly why this section stays general and a physiotherapy assessment matters.
- For disc-related sciatica: gentle extension exercises are often helpful, following the same directional-preference principle described in Carenyx's slip disc article.
- For stenosis-related sciatica: flexion-based exercises (such as a gentle seated forward lean, or exercises performed in a slightly bent-forward position) and a stationary bicycle (which naturally keeps the spine in a forward-leaning position) are often better tolerated and more helpful than extension-based exercises.
- For piriformis-related sciatica: specific piriformis stretches, usually involving crossing the affected leg and gently rotating the hip, along with general hip and gluteal strengthening.
- Walking, at a comfortable pace and distance, remains broadly helpful across most causes of sciatica, with the caveat that stenosis-related sciatica may specifically limit walking distance before symptoms appear — which is itself useful information to share with your doctor, not just a limitation to push through.
Recovery Timeline
Many people improve substantially within 6–12 weeks with appropriate conservative treatment, especially when a disc is the cause, and some see meaningful improvement sooner. Stenosis-related symptoms often improve more slowly, particularly in older adults, though this varies considerably between individuals.
If surgery becomes necessary, recovery timelines are broadly similar to those described in Carenyx's slip disc article for microdiscectomy, or somewhat longer for stenosis decompression surgery or a fusion procedure, depending on the specific surgery performed. Your surgical team's specific guidance for your procedure should always take priority over these general ranges.
Prevention
Most prevention strategies for sciatica overlap directly with prevention of its most common underlying causes:
- Maintain core and back strength to support your lower spine.
- Avoid prolonged sitting without breaks, and be mindful of sitting posture, particularly if you're prone to piriformis-related symptoms.
- Practice safe lifting technique to reduce disc herniation risk.
- Stay generally active with low-impact exercise such as walking or swimming.
- Manage body weight and blood sugar, particularly relevant given diabetes's link to sciatica risk.
- Don't smoke, supporting disc health independent of its many other benefits.
Frequently Asked Questions
Is sciatica the same as a slipped disc? Not exactly. A slipped disc is one common cause of sciatica, but sciatica can also come from spinal stenosis, a slipped vertebra, or a tight piriformis muscle. Sciatica describes the pattern of nerve pain; a slipped disc is one possible reason for it.
How long does sciatica usually last? Many people improve substantially within 6–12 weeks with appropriate treatment (stenosis-related symptoms often more slowly), though the exact timeline depends on the underlying cause and how early appropriate treatment starts.
Can sciatica go away on its own without treatment? Many milder cases improve over time even without formal treatment, but "conservative treatment" — staying appropriately active, targeted exercise, and pain management — genuinely speeds and improves that recovery rather than simply waiting it out.
Is walking good or bad for sciatica? Generally good, for most causes and most people — but if walking specifically and consistently triggers your symptoms (a pattern that suggests spinal stenosis), that specific pattern is important information for your doctor, not something to simply push through.
Can sciatica affect both legs at the same time? It can, though it's less common than one-sided sciatica. Sciatica in both legs, or alternating sides, can signal cauda equina syndrome — seek same-day care, especially if combined with any of the red flag symptoms listed earlier.
Does sciatica mean I need an MRI right away? Not usually, for a first episode without red flags. Most guidelines recommend a period of conservative treatment first, with imaging reserved for cases that don't improve, have red flags, or need surgical planning.
What's the difference between sciatica and piriformis syndrome? Piriformis syndrome is one specific, less common cause of sciatica-like symptoms, where a tight piriformis muscle in the buttock irritates the sciatic nerve, rather than a problem in the spine itself. It's usually considered after spinal causes have been reasonably ruled out.
Can pregnancy cause sciatica? Yes — pregnancy can cause sciatica-like symptoms through a combination of postural changes, weight distribution, and sometimes direct pressure from the growing uterus on pelvic nerves. This is generally managed conservatively and most often resolves after delivery, though it should still be discussed with your obstetric care team.
How do I know if it's sciatica or just a hip problem? True sciatica typically radiates below the knee and often gets worse with sitting, coughing, or sneezing. Hip problems more often affect the groin or outer thigh and worsen with specific hip movements rather than these back-related triggers. This is a genuinely useful distinction to describe clearly to your doctor, but an exam is still the reliable way to tell them apart — see the differential diagnosis section above.
Is it safe to use a heating pad or ice for sciatica? Either can provide symptomatic comfort for many people, and there's no strong evidence that one is clearly superior to the other for sciatica specifically. Use whichever provides you more relief, avoiding direct skin contact with either for extended periods to prevent burns or cold injury.
Myths vs. Facts
Myth: Sciatica is a diagnosis by itself. Fact: Sciatica is a pattern of symptoms with an underlying cause — most often a disc herniation, but sometimes spinal stenosis, spondylolisthesis, or piriformis syndrome. Effective treatment depends on identifying which one applies to you.
Myth: All buttock or leg pain is sciatica. Fact: True sciatica follows a specific pattern along the sciatic nerve's path, usually one-sided, often reaching below the knee. Many causes of buttock and leg pain — hip joint problems, muscular strains, and other conditions — are not sciatica at all and need different treatment.
Myth: Sitting is always bad for sciatica. Fact: It depends on the cause. Sitting often worsens disc-related sciatica but can actually relieve stenosis-related sciatica. This is exactly why understanding the underlying cause changes practical daily advice, not just formal treatment.
Myth: You should stretch aggressively through sciatic pain to "loosen the nerve." Fact: Aggressive stretching into pain can worsen nerve irritation. Gentle, specific, directionally appropriate exercise — not aggressive stretching — is what the evidence actually supports.
Myth: Sciatica always eventually requires surgery. Fact: The large majority of sciatica, regardless of underlying cause, improves with conservative treatment alone. Surgery is reserved for specific situations described earlier in this article, not a default eventual outcome.
Glossary
- Cauda equina syndrome: a surgical emergency caused by severe compression of the bundle of nerves at the bottom of the spinal cord, causing bladder/bowel dysfunction, saddle numbness, and leg weakness.
- Decompression surgery: surgery that enlarges the space available for a compressed nerve root or the spinal cord, commonly used for spinal stenosis.
- Epidural steroid injection: a targeted anti-inflammatory injection given near a spinal nerve root.
- Hip osteoarthritis: wear-and-tear arthritis of the hip joint, which can cause groin, outer thigh, or knee pain sometimes mistaken for sciatica.
- Laminectomy: a type of decompression surgery that removes part of the bony arch (lamina) of a vertebra to relieve pressure on the spinal canal.
- Microdiscectomy: the standard surgical procedure to remove herniated disc material pressing on a nerve.
- Peripheral neuropathy: nerve damage, often from conditions like diabetes, typically causing symmetrical numbness and tingling in both feet and legs.
- Piriformis muscle: a muscle deep in the buttock, beneath which the sciatic nerve normally passes.
- Piriformis syndrome: a condition where a tight or spasming piriformis muscle irritates the sciatic nerve, causing sciatica-like symptoms.
- Sciatic nerve: the longest and widest nerve in the body, formed from the L4 to S3 nerve roots, running from the pelvis down the back of the leg.
- Spinal fusion: surgery that permanently joins two or more vertebrae together, sometimes performed alongside decompression for spinal instability.
- Spinal stenosis: narrowing of the spinal canal or the openings where nerve roots exit the spine, which can compress nerves.
- Spondylolisthesis: a condition where one vertebra slips forward relative to the vertebra below it.
- Trochanteric bursitis: inflammation of a fluid-filled cushion at the outer hip, causing localized outer hip and thigh pain sometimes mistaken for sciatica.
- Vascular claudication: leg pain caused by reduced blood flow (often from peripheral artery disease), triggered by walking and relieved by rest.
References (Vancouver Style)
Reference list reviewed November 2026. Each source links to its PubMed record, the guideline's official page, or a PubMed search for the exact title.
- National Institute for Health and Care Excellence. Low back pain and sciatica in over 16s: assessment and management. NICE guideline NG59. London: NICE; 2016 (updated 2020). Link Link
- Koes BW, van Tulder MW, Peul WC. Diagnosis and treatment of sciatica. BMJ. 2007;334(7607):1313-1317. Link Link
- Genevay S, Atlas SJ. Lumbar spinal stenosis. Best Pract Res Clin Rheumatol. 2010;24(2):253-265. Link Link
- Stewart JD. The piriformis syndrome is overdiagnosed. Muscle Nerve. 2003;28(5):644-646. Link Link
- Fishman LM, Dombi GW, Michaelsen C, et al. Piriformis syndrome: diagnosis, treatment, and outcome — a 10-year study. Arch Phys Med Rehabil. 2002;83(3):295-301. Link Link
- Konstantinou K, Dunn KM. Sciatica: review of epidemiological studies and prevalence estimates. Spine. 2008;33(22):2464-2472. Link Link
- Battié MC, Videman T, Gill K, et al. Smoking and lumbar intervertebral disc degeneration: an MRI study of identical twins. Spine. 1991;16(9):1015-1021. Link Link
- Gardner A, Gardner E, Morley T. Cauda equina syndrome: a review of the current clinical and medico-legal position. Eur Spine J. 2011;20(5):690-697. Link Link
- Brinjikji W, Luetmer PH, Comstock B, et al. Systematic literature review of imaging features of spinal degeneration in asymptomatic populations. AJNR Am J Neuroradiol. 2015;36(4):811-816. Link Link
- Dahm KT, Brurberg KG, Jamtvedt G, Hagen KB. Advice to rest in bed versus advice to stay active for acute low-back pain and sciatica. Cochrane Database Syst Rev. 2010;(6):CD007612. Link Link
- Pinto RZ, Maher CG, Ferreira ML, et al. Epidural corticosteroid injections in the management of sciatica: a systematic review and meta-analysis. Ann Intern Med. 2012;157(12):865-877. Link Link
- May S, Donelson R. Evidence-informed management of chronic low back pain with the McKenzie method. Spine J. 2008;8(1):134-141. Link Link
- Choi BK, Verbeek JH, Tam WW, Jiang JY. Exercises for prevention of recurrences of low-back pain. Cochrane Database Syst Rev. 2010;(1):CD006555. Link Link
Related Articles
- Understanding Slip Disc: Causes, Symptoms, Diagnosis and Treatment
- Spinal Stenosis
Call to Action
If your leg pain follows the pattern described in this article, the most useful next step is figuring out why — not guessing at generic back exercises.
Take the free Spine Health Index → — an 11-pillar assessment of your overall spine health.
Request a consultation with Dr. Vishal Nigam → — a proper diagnosis of the underlying cause is the difference between an exercise program that helps and one that doesn't.