Executive Summary
"Deformity of spine" describes an abnormal spinal curvature — most commonly scoliosis (a sideways curve) or kyphosis (an exaggerated forward curve). These conditions affect different age groups for genuinely different reasons: adolescent idiopathic scoliosis develops during growth with no single known cause, while adult scoliosis either represents a curve carried forward from adolescence or a distinct, separate condition — degenerative scoliosis — that develops later in life from ordinary spinal aging.
Here is what the evidence actually shows: most mild spinal curves need only monitoring, not active treatment. For adolescents with progressive curves, real, landmark research confirms bracing significantly reduces the likelihood of a curve becoming severe enough to need surgery. For adults, treatment goals genuinely differ — the focus shifts toward pain relief and maintaining function and independence, rather than maximal curve correction.
This article explains what spinal deformity actually is, how it differs across age groups, how doctors diagnose and measure it, every real treatment option, and what living with it actually looks like — in plain language, backed by real evidence, reviewed by a spine surgeon.
Red Flags: When This Is a Medical Emergency
⚠ Go to a hospital emergency department now — do not wait for a clinic appointment — if you have (or your child has):
- Back pain accompanied by fever
- New or progressive numbness, tingling, or weakness in the legs
- Loss of bladder or bowel control
- Sudden, significant back pain
See a spine specialist within 1–2 weeks if you have (or your child has):
- A curve that is worsening
- Kyphosis or scoliosis appearing before age 10, which — unlike the more common adolescent pattern — warrants more thorough evaluation for an underlying cause.
- A painful curve, back pain that wakes your child at night, or a left-sided upper-back curve
Read the full article14 min · causes, tests, treatment, exercises, questions
Introduction
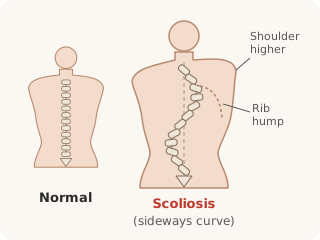
A healthy spine, viewed from the side, has gentle natural curves; viewed from behind, it should appear essentially straight. "Spinal deformity" describes a meaningful departure from this normal pattern — most often a sideways curve (scoliosis) or an excessive forward curve of the upper back (kyphosis). These aren't rare, exotic conditions — mild degrees of spinal curvature are genuinely common, and most never require anything beyond periodic observation.
This article covers the three real, distinct situations most people encounter: adolescent idiopathic scoliosis (the most common form, developing during growth), adult scoliosis (either a persisting adolescent curve or a separate, degenerative condition developing later in life), and kyphosis.
Normal Spinal Alignment
Viewed from the side, a healthy spine has three real, natural curves: a gentle forward curve in the neck, a gentle backward curve in the upper back, and a gentle forward curve in the lower back — together allowing the spine to absorb load efficiently while keeping your head balanced over your pelvis. Viewed from behind, a healthy spine appears straight, without meaningful side-to-side curvature.
Doctors measure the degree of any abnormal curve using the Cobb angle — drawing lines along the most tilted vertebrae at the top and bottom of a curve on an X-ray, and measuring the angle between them. This single, standardized, real measurement is the foundation for nearly every real diagnostic and treatment decision in spinal deformity.
Adolescent Idiopathic Scoliosis: How It Develops
"Idiopathic" means the exact cause isn't known — despite extensive research, no single cause has been identified, though genetics clearly play a real role, since the condition runs in families more than chance alone would predict. It typically develops or progresses during the adolescent growth spurt, which is why monitoring focuses specifically on the years a child is still actively growing.
Real, established risk factors for curve progression include:
- Being female — girls are significantly more likely than boys to have curves that progress to a degree requiring treatment.
- A larger curve at initial diagnosis.
- Remaining significant growth still ahead (assessed via a real, standardized skeletal maturity measure called the Risser sign, and, in girls, whether menstruation has started).
- A family history of scoliosis requiring treatment.
Real, published epidemiology shows that scoliosis of 10° or more affects about 2–3% of adolescents; curves over 40° are rare (about 1 in 1,000). Much milder curves are considerably more common.
Adult Scoliosis: Two Genuinely Different Situations
Adult scoliosis is not one single condition — real, current understanding distinguishes two genuinely different situations that happen to share a similar appearance:
Adult Idiopathic Scoliosis — a curve that began during adolescence and has persisted, and sometimes slowly progressed, into adulthood. The underlying curve itself is the same real condition as adolescent idiopathic scoliosis, just carried forward. Real, current classification systems further subdivide this group by age — younger adults (roughly 19-30) tend to have more flexible curves that behave somewhat differently from those in older adults (over 45-60), whose curves have typically stiffened and accumulated additional degenerative change on top of the original adolescent curve.
Adult Degenerative ("de novo") Scoliosis — a genuinely distinct condition, developing for the first time in adulthood as a consequence of ordinary spinal aging — disc degeneration, facet joint arthritis, and disc height loss on one side more than the other gradually pulling the spine out of alignment. This is commonly, and specifically, defined as a coronal Cobb angle greater than 10° in someone aged 18 or older, together with real, visible degenerative features on imaging — disc height loss, bone spurs, and facet joint arthritis — not simply an incidental, isolated curve finding.
This is not simply "adolescent scoliosis showing up late" — it has a different real cause, and real, published research notes it is "not merely a curve problem," but a more complex situation where the deformity itself, pain, and — in some cases — nerve compression and other age-related health conditions all interact.
This distinction matters clinically: adult degenerative scoliosis very commonly coexists with, or is complicated by, other real, age-related spine conditions — particularly spinal stenosis and degenerative spondylolisthesis — and often occurs alongside broader health considerations like osteoporosis, reduced muscle mass, or diabetes that genuinely affect treatment planning. Real, current clinical thinking specifically emphasizes that treatment goals for this group shift meaningfully compared to adolescent care — away from maximal curve correction, and toward symptom relief, durable day-to-day function, and preserving independence, given the real, broader health context many adult patients bring to treatment decisions.
Kyphosis
Kyphosis describes an excessive forward curve of the upper back — everyone has some natural forward curve there, but kyphosis describes a curve significant enough to be considered abnormal. In adolescents, the most common real cause is Scheuermann's disease, a structural condition affecting how the vertebrae form during growth, causing them to develop a real, wedge-like shape rather than their normal rectangular shape — this wedging, repeated across several vertebrae, produces the characteristic rounded curve.
Real, current SRS and SOSORT guidelines: bracing is generally considered for Scheuermann's kyphosis between about 45° and 75° in children still growing, alongside real, visible wedging on X-ray; larger or painful rigid curves may need surgery — a real, similar logic to scoliosis bracing, timed to the growth window when treatment can still meaningfully influence the curve's development.
In older adults, kyphosis is often related to osteoporotic vertebral compression fractures (see CARENYX's dedicated Osteoporosis article) or general age-related postural and disc changes, sometimes called "postural kyphosis" when it's flexible and correctable, as distinct from the more structurally fixed kyphosis of Scheuermann's disease or multiple compression fractures. This distinction matters for treatment — postural kyphosis often responds well to targeted strengthening and mobility exercise, while structurally fixed kyphosis from vertebral fractures or Scheuermann's disease has more limited real potential for exercise alone to reverse, though exercise remains valuable for pain, function, and preventing further progression regardless of the underlying cause.
In India, tuberculosis of the spine is an important cause of a sharp, angular hump in children and adults, often with back pain, fever, weight loss or night sweats. It needs urgent assessment.
Symptoms: What Spinal Deformity Actually Feels Like
Real, common signs of scoliosis, particularly in adolescents, include:
- Uneven shoulders or shoulder blade height
- One side of the rib cage appearing more prominent, especially when bending forward
- Uneven waistline or hip height
- The body leaning slightly to one side
Adolescent scoliosis itself is often not painful — this is a genuinely important, real point, since parents and adolescents sometimes reasonably assume no pain means no problem, when in fact significant curves can exist without any pain at all. Adult scoliosis, particularly degenerative scoliosis, much more commonly does cause real pain, along with the visible signs above.
Diagnosis: How Doctors Confirm Spinal Deformity
Diagnosis begins with a physical examination, including the real, standard "Adam's forward bend test" — bending forward at the waist, which makes any rib or waist asymmetry more visible. If scoliosis is suspected, a standing X-ray confirms the diagnosis and allows the real Cobb angle measurement described above.
For adolescents, doctors also assess skeletal maturity (via the Risser sign and menstrual history in girls) to estimate how much growth remains — a real, critical factor in predicting whether a curve is likely to progress further. For adults, especially with degenerative scoliosis, additional imaging (MRI) is often needed to assess for coexisting spinal stenosis or nerve involvement, which frequently drives the actual symptoms more than the curve itself.
Treatment Options by Curve Severity and Age
For adolescents:
- Curves under 25°: real, current guidance generally recommends observation alone, with periodic X-rays to monitor for progression.
- Curves of 25-40°, with significant growth remaining: real, evidence-based bracing is generally recommended. The 2013 BrAIST trial found 72% success with bracing versus 48% with observation alone. Teens who wore the brace at least about 13 hours a day had roughly 90% success — the more hours worn, the better.
- Curves over about 45–50°, or curves continuing to progress despite bracing: surgery (spinal fusion) is generally considered.
Physiotherapeutic Scoliosis-Specific Exercises (PSSE), such as the Schroth method, have real, growing evidentiary support as a conservative option, particularly for milder curves or alongside bracing — genuinely distinct from generic core-strengthening exercise, since these programs are specifically designed around an individual's own curve pattern.
For adults, treatment goals genuinely shift. Real, current guidance for adult degenerative scoliosis specifically emphasizes:
- Pain management and physical therapy as first-line treatment, often addressing coexisting stenosis symptoms alongside the deformity itself.
- PSSE-style exercise, now being studied specifically in adults with encouraging early real interest, not only adolescents.
- Surgery, reserved for adults with significant, persistent pain or neurological symptoms not responding to conservative care — real, current surgical planning for adults is genuinely more complex than adolescent scoliosis surgery, often needing to account for degenerative changes, bone quality, and overall health alongside the curve itself.
Exercises
Real, evidence-informed exercise for spinal deformity should generally be guided by a physiotherapist familiar with PSSE principles for anything beyond general conditioning. CARENYX's own reviewed Exercise Library includes generally appropriate supporting options:
- Thoracic Mobility and Thoracic Rotation — general mobility support.
- Bird Dog and Bridge — general core support relevant to both scoliosis and kyphosis management.
See the full Spine Fitness Hub for the complete, curated collection — though for scoliosis specifically, a real, individualized PSSE program from a qualified physiotherapist, rather than generic exercise alone, is the appropriately evidence-matched approach.
Recovery Timeline
For adolescents treated with bracing, real, typical treatment continues through the remaining growth period, with brace weaning once skeletal maturity is reached. After spinal fusion surgery (either age group), real, typical recovery involves several weeks of activity restriction, gradual return to normal activity over 3-6 months, and continued improvement over the following year as fusion fully consolidates.
Prevention
Adolescent idiopathic scoliosis is not currently preventable, since its cause isn't fully understood — this is a real, important point for parents to know, since it isn't caused by backpacks, posture, or anything a family did or didn't do. For adult degenerative scoliosis, maintaining general spine health — the same real measures described throughout CARENYX's Spine Fitness Hub — may help support spinal stability as aging changes occur, though it cannot fully prevent age-related degeneration.
Living With Spinal Deformity Long-Term
For adolescents who complete bracing successfully, most go on to live full, active lives with no meaningful ongoing restriction once skeletal maturity is reached — the treatment goal is specifically to reach adulthood with a curve that won't require surgery later, and successful bracing genuinely achieves this for most adherent patients. Periodic monitoring into early adulthood is still real, reasonable practice, since a small minority of curves do continue slowly progressing even after growth stops.
For adults living with either idiopathic or degenerative scoliosis, the real, ongoing management picture centers on staying functionally active, managing pain through the real, evidence-based measures described above, and monitoring for any new neurological symptoms that might indicate progression or nerve involvement requiring reassessment. A real, important and often reassuring point: many adults live for decades with a stable, non-progressive curve, requiring nothing beyond periodic check-ins with their spine specialist.
Real, current thinking in adult spinal deformity care also emphasizes a genuinely collaborative approach — since many adult patients, particularly those with degenerative scoliosis, are also managing other real health conditions, treatment planning benefits from coordination between your spine specialist and your other treating doctors, rather than viewing the spine in isolation from your overall health.
Frequently Asked Questions
Did my child's scoliosis happen because of their backpack or posture? No — real, current evidence does not support backpacks, posture, sitting habits, or sports as causes of adolescent idiopathic scoliosis; its real cause remains genuinely unknown, with genetics playing a contributing role.
Will scoliosis get worse after growth stops? For adolescent idiopathic scoliosis, progression significantly slows once skeletal maturity is reached — this is exactly why the growing years are the real, critical monitoring and treatment window. Adult idiopathic scoliosis can still slowly progress over subsequent decades, though generally much more slowly than during adolescence. Curves above about 50° at skeletal maturity can keep progressing about 1° a year and need periodic follow-up.
Is adult degenerative scoliosis the same condition as my teenage scoliosis, just worse? Not necessarily — if you never had scoliosis as a teenager, adult degenerative scoliosis is a genuinely separate, distinct condition caused by spinal aging, not a delayed version of adolescent scoliosis.
Does wearing a brace hurt? Braces are generally not painful when properly fitted, though there's a real, genuine adjustment period, and proper, professional fitting matters significantly for both comfort and effectiveness.
Can exercise alone fix scoliosis? For milder curves, evidence-based PSSE programs can meaningfully help, but real, current evidence doesn't support exercise alone as a substitute for bracing in curves that meet real bracing criteria, or for surgery in curves that meet real surgical criteria.
Is scoliosis surgery safe? Modern spinal fusion for scoliosis, performed by an experienced surgeon, has a real, well-established track record for appropriately selected patients — like any major surgery, it carries real risks your surgeon will discuss specifically with you and your individual situation.
Can kyphosis be corrected with exercise alone? This depends on the real, underlying cause — flexible, postural kyphosis often responds well to targeted strengthening and mobility work, while structurally fixed kyphosis from Scheuermann's disease or vertebral compression fractures has more limited potential for exercise to reverse on its own, though exercise still meaningfully helps with pain and function in both situations.
How often does my child need X-rays while being monitored for scoliosis? Real, typical monitoring intervals are every 4-6 months during active growth, since this is the real window where meaningful progression is most likely — your doctor will adjust this specific interval based on your child's actual curve size, age, and remaining growth potential, since a younger child with more growth ahead generally needs closer, more frequent monitoring than an adolescent nearing skeletal maturity.
Myths vs. Facts
Myth: "Scoliosis is caused by carrying a heavy backpack or bad posture." Fact: Real, current evidence does not support this — adolescent idiopathic scoliosis has no single known cause, and genetics play a real, contributing role instead.
Myth: "All scoliosis eventually needs surgery." Fact: The large majority of scoliosis cases — particularly milder curves — are managed with observation alone or bracing, never requiring surgery.
Myth: "Adult scoliosis is rare." Fact: Real, published estimates suggest adult degenerative scoliosis is genuinely more common than many people realize, and its actual incidence is higher than adolescent idiopathic scoliosis in some real population studies.
Glossary
- Cobb angle — the standard, real measurement of spinal curve severity on X-ray.
- Risser sign — a real, standardized measure of skeletal maturity, used to guide adolescent scoliosis treatment decisions.
- Idiopathic — meaning the specific cause is unknown.
- De novo degenerative scoliosis — adult scoliosis developing newly, from spinal aging, without a prior adolescent curve.
- PSSE — Physiotherapeutic Scoliosis-Specific Exercises, such as the Schroth method.
- Kyphosis — an excessive forward curve of the upper spine.
References (Vancouver Style)
Reference list reviewed November 2026. Each source links to its PubMed record, the guideline's official page, or a PubMed search for the exact title.
- Weinstein SL, Dolan LA, Wright JG, Dobbs MB. Effects of bracing in adolescents with idiopathic scoliosis. N Engl J Med. 2013;369(16):1512-1521. Link
- Negrini S, Donzelli S, Aulisa AG, et al. 2016 SOSORT guidelines: orthopaedic and rehabilitation treatment of idiopathic scoliosis during growth. Scoliosis Spinal Disord. 2018;13:3. Link
- Kuznia AL, Hernandez AK, Lee LU. Adolescent idiopathic scoliosis: common questions and answers. Am Fam Physician. 2020;101(1):19-23. Link
Related Articles
- Osteoporosis
- Degenerative Disc Disease
- Spinal Stenosis
- Spine Fitness Hub
- 112 Real Neck & Back Pain FAQs
Call to Action
If you or your child have noticed uneven shoulders, an uneven waistline, or a visible spinal curve, book a consultation with CARENYX's spine team for a proper evaluation and, if needed, a real, individualized treatment plan.