Executive Summary
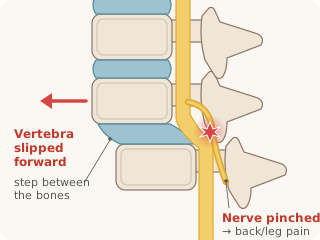
Spondylolisthesis is the forward slippage of one vertebra over the one below it — most commonly in the lower back, at the L4-L5 or L5-S1 levels. Real, current guidance is that many cases, particularly lower-grade slippage, cause no significant symptoms at all, and treatment decisions are based on your actual symptoms, not the slippage percentage alone.
Here is what the evidence actually shows: nonsurgical treatment is the appropriate first approach for most patients, and for degenerative spondylolisthesis with stenosis needing surgery, older NASS (2014) guidance suggested adding fusion. Newer large trials show decompression alone works as well for many patients with a stable slip. Fusion is usually added when there is instability on bending X-rays, significant deformity or mechanical back pain — an individual decision with your surgeon.. This article explains what spondylolisthesis actually is, the real grading system doctors use, how it's diagnosed, and every real treatment option.
Red Flags: When This Is a Medical Emergency
⚠ See a doctor immediately if you have:
- Loss of bladder or bowel control
- Numbness in the saddle area
- Progressive leg weakness
In rare, extreme cases, spondylolisthesis can contribute to cauda equina syndrome — a genuine emergency covered in CARENYX's dedicated Cauda Equina Syndrome article.
Read the full article5 min · causes, tests, treatment, exercises, questions
Introduction
"Spondylolisthesis" comes from Greek words meaning vertebra and slippage — a genuinely literal description of the condition. It's a distinct condition from spondylolysis (a stress fracture in a small bony bridge called the pars interarticularis), though spondylolysis can be a real precursor: the fracture can destabilize the vertebra enough to let it slip forward, becoming spondylolisthesis.
How Spondylolisthesis Develops
Real, distinct types include:
- Isthmic spondylolisthesis — from a spondylolysis stress fracture, often starting in adolescence, sometimes related to repetitive extension activities in sports like gymnastics.
- Degenerative spondylolisthesis — from age-related disc and facet joint changes reducing spinal stability, typically appearing after age 50.
- Dysplastic spondylolisthesis — from a congenital difference in vertebral shape, present from birth and treated more aggressively given a higher real risk of neurological injury.
Grading: The Real, Standard Classification
Doctors grade spondylolisthesis using the real, standard Meyerding classification, based on the percentage of forward slippage:
- Grade I: less than 25% slippage
- Grade II: 25-50%
- Grade III: 50-75%
- Grade IV: 75-100%
- Grade V: greater than 100% (complete displacement, sometimes called spondyloptosis)
A real, important point: symptom severity doesn't always match the grade — some people with Grade I slippage have significant pain, while others with more advanced slippage remain comfortable. Real, published data shows higher-grade slippage (Grade III-IV) is more consistently associated with symptoms: back pain in 55-91% of these patients, radiating leg symptoms in 44-55%.
Symptoms: What Spondylolisthesis Actually Feels Like
Real, common symptoms include:
- Lower back pain, often worse with bending, twisting, or standing, and sometimes eased by sitting
- Pain radiating into the buttocks or legs, if a nerve root is affected
- A sense of leg weakness or tightness in the hamstrings
- In degenerative spondylolisthesis specifically, symptoms of spinal stenosis (leg pain worse with walking, better with sitting or leaning forward) are common, since the two conditions frequently occur together
Diagnosis: How Doctors Confirm Spondylolisthesis
Real, current NASS guidance identifies a standing lateral X-ray as the most appropriate, first real diagnostic test, since standing specifically shows real, weight-bearing slippage that can be less apparent lying down. MRI is added when there's leg pain or suspected nerve involvement, to evaluate for accompanying spinal stenosis. Flexion–extension (bending) X-rays may be taken to check for instability.
Treatment Options
Nonsurgical treatment is the appropriate first approach for most patients., including physical therapy focused on core stabilization, activity modification, and short-term anti-inflammatory medication for flares. Take NSAIDs only on a doctor's or pharmacist's advice, at the lowest dose for the shortest time. Avoid them, or check first, if you have kidney disease, stomach ulcer or acidity, heart disease or high BP, take blood thinners, are pregnant, or are over 65.
Surgery is considered for high-grade slips (over 50%) in children and teens, and in adults for progressive nerve symptoms or persistent symptoms after about 3 months of proper non-surgical care. For degenerative spondylolisthesis with stenosis, older NASS (2014) guidance suggested adding fusion. Newer large trials show decompression alone works as well for many patients with a stable slip. Fusion is usually added when there is instability on bending X-rays, significant deformity or mechanical back pain — an individual decision with your surgeon.. For isthmic spondylolisthesis in adults needing surgery, fusion is generally recommended for better real, long-term outcomes.
Exercises
Real, evidence-based exercise for spondylolisthesis centers on core stabilization, avoiding excessive spinal extension for isthmic cases specifically (since extension can worsen the underlying stress fracture pattern). CARENYX's own reviewed Exercise Library includes relevant, appropriate options:
- Bird Dog, Dead Bug, and Bridge — real, core-focused exercises appropriate for most spondylolisthesis presentations.
- Pelvic Tilts — a gentle, foundational option.
A physiotherapist's individual guidance matters more here than for most spine conditions, given the real, meaningful difference in appropriate exercise selection between isthmic and degenerative types.
Frequently Asked Questions
Does spondylolisthesis always get worse over time? Not necessarily — many cases, especially lower-grade slippage, remain stable for years with appropriate management, though real, periodic monitoring is reasonable, particularly during adolescent growth for isthmic cases.
Can I still exercise with spondylolisthesis? Generally yes, with appropriate, individualized guidance — core stabilization is genuinely beneficial, though certain movements (particularly repetitive spinal extension for isthmic types) may need real, specific modification.
Is spondylolisthesis the same as a slipped disc? No — a slipped disc (herniation) involves disc material pushing out; spondylolisthesis involves the entire vertebra slipping forward. They're genuinely different conditions, sometimes occurring together.
Glossary
- Meyerding grading — the real, standard classification of slippage severity, Grade I through V.
- Isthmic spondylolisthesis — slippage from a pars interarticularis stress fracture.
- Degenerative spondylolisthesis — slippage from age-related spinal changes.
- Pars interarticularis — the small bony bridge whose fracture (spondylolysis) can lead to spondylolisthesis.
References (Vancouver Style)
Reference list reviewed November 2026. Each source links to its PubMed record, the guideline's official page, or a PubMed search for the exact title.
- Matz PG, Meagher RJ, Lamer T, et al. Guideline summary review: an evidence-based clinical guideline for the diagnosis and treatment of degenerative lumbar spondylolisthesis. Spine J. 2016;16(3):439-448. Link
- Weinstein JN, Lurie JD, Tosteson TD, et al. Surgical versus nonsurgical treatment for lumbar degenerative spondylolisthesis. N Engl J Med. 2007;356(22):2257-2270. Link
- Försth P, Ólafsson G, Carlsson T, et al. A randomized, controlled trial of fusion surgery for lumbar spinal stenosis. N Engl J Med. 2016;374(15):1413-1423. Link
- Tenny S, Hanna A, Gillis CC. Spondylolisthesis. StatPearls. Treasure Island (FL): StatPearls Publishing. Link
Call to Action
If you have persistent lower back pain with leg symptoms, book a real consultation with CARENYX's spine team for proper evaluation and grading.